Neurogenic Bladder
The bladder does not work properly because of a nerve problem.
What is Neurogenic Bladder?
The bladder stores urine at low pressure and empties completely when the child chooses. Both parts depend on nerves running from the spinal cord. When those nerves are affected, the bladder becomes neurogenic — it may hold too little, squeeze at high pressure, fail to empty, or leak continuously.
The commonest cause in children is spina bifida and other spinal cord abnormalities, including a tethered cord. It can also follow spinal injury, tumours or some neurological conditions.
The important point for parents is that wetting is not the main danger. High pressure inside the bladder is what damages the kidneys, and that pressure can be present in a child who appears merely to be wet.
With proper management most children can be kept dry and, more importantly, keep healthy kidneys into adult life.

In your language
Neurogenic Bladder
The bladder does not work properly because of a nerve problem.
The bladder stores urine at low pressure and empties completely when the child chooses. Both parts depend on nerves running from the spinal cord. When those nerves are affected, the bladder becomes neurogenic — it may hold too little, squeeze at high pressure, fail to empty, or leak continuously.
நரம்பு சார்ந்த சிறுநீர்ப்பை கோளாறு
நரம்பு பாதிப்பால் சிறுநீர்ப்பை சரியாக செயல்படாத நிலைதான் நியூரோஜெனிக் பிளாடர். முதுகுத் தண்டுவட குறைபாடு (spina bifida) உள்ள குழந்தைகளில் இது அதிகம். சிறுநீர் கசிவை விட, சிறுநீர்ப்பைக்குள் அதிக அழுத்தம் இருப்பதே சிறுநீரகத்திற்கு ஆபத்து. சுத்தமான இடைவெளி வடிகுழாய் (CIC), மருந்துகள், மலச்சிக்கல் சிகிச்சை ஆகியவை முக்கியம் — பெற்றோரே இதைச் செய்யக் கற்றுக்கொள்ளலாம். குழந்தையின் முதுகின் கீழ்ப்பகுதியில் குழி, முடி, அல்லது வீக்கம் இருந்தால் கண்டிப்பாக பரிசோதிக்கவும்.
നാഡീസംബന്ധമായ മൂത്രസഞ്ചി തകരാറ്
നാഡികളുടെ തകരാറു മൂലം മൂത്രസഞ്ചി ശരിയായി പ്രവർത്തിക്കാത്ത അവസ്ഥയാണ് ന്യൂറോജെനിക് ബ്ലാഡർ. സ്പൈന ബൈഫിഡ ഉള്ള കുട്ടികളിലാണ് ഇത് കൂടുതൽ. മൂത്രം പോകുന്നതിനെക്കാൾ അപകടം മൂത്രസഞ്ചിയിലെ ഉയർന്ന മർദ്ദമാണ് — അത് വൃക്കയെ നശിപ്പിക്കും. ശുദ്ധമായ ഇടവിട്ടുള്ള കത്തീറ്ററൈസേഷൻ (CIC), മരുന്നുകൾ, മലബന്ധ ചികിത്സ എന്നിവയാണ് പ്രധാനം — മാതാപിതാക്കൾക്ക് ഇത് പഠിക്കാം. കുട്ടിയുടെ നടുവിന്റെ താഴ്ഭാഗത്ത് കുഴി, രോമം, വീക്കം എന്നിവയുണ്ടെങ്കിൽ പരിശോധിക്കണം.
What Parents Notice
Not every child shows every sign. If something on this list matches your child, it is worth an examination rather than a guess.
- Continuous or frequent wetting, or never achieving toilet training at the expected age
- Straining to pass urine, a poor stream, or the sense that the bladder is never empty
- Repeated urinary tract infections
- Constipation and soiling, which almost always accompany a neurogenic bladder
- A dimple, hairy patch, swelling or birthmark over the lower back
- Weakness, altered sensation or foot deformity in the legs
- Kidney swelling found on a scan
How It Is Confirmed
- Ultrasound of the kidneys and bladder, including how much urine is left behind after voiding
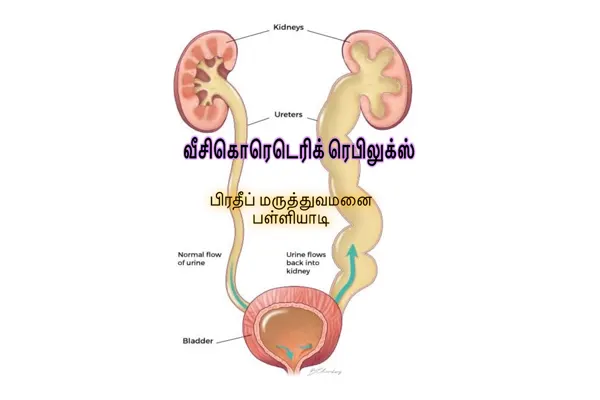
- MCUG to check for reflux and to assess bladder shape
- Urodynamic study — the key test, measuring bladder pressure, capacity and leak point, which is what determines whether the kidneys are at risk
- MRI of the spine when a spinal cause is suspected
- Blood tests for kidney function, and a DMSA scan for scarring
- A bladder and bowel diary kept by the family, which is genuinely useful information
How It Is Treated
- Clean intermittent catheterisation (CIC): a fine catheter is passed several times a day to empty the bladder. Parents learn it, and older children do it themselves. It is the single most effective measure for protecting kidneys and achieving dryness.
- Anticholinergic or similar medication to lower bladder pressure and increase capacity.
- Managing constipation with a proper bowel programme — a loaded bowel makes bladder function worse and is often the missing piece.
- Preventive antibiotics in selected children, and prompt treatment of infections.
- Botulinum toxin injection into the bladder muscle for a bladder that stays high-pressure despite medication.
- Surgery in selected children: bladder augmentation to create a larger low-pressure reservoir, a catheterisable channel (Mitrofanoff) to make CIC easier, or procedures to improve outlet resistance.
- Care is shared — paediatric surgery, neurosurgery where relevant, physiotherapy and the family working together over years.
Does My Child Need Surgery?
Not every child with Neurogenic Bladder needs an operation. These are the situations in which surgery is advised — and the decision is always made after examining your child, never from a description alone.
Bladder pressure stays high despite catheterisation and medication
The kidneys show worsening swelling, scarring or falling function
Reflux persists and infections keep recurring
Incontinence remains socially disabling despite full conservative management
A tethered cord or other spinal lesion needs neurosurgical release — assessed alongside the urological plan
What Happens Over Time
With catheterisation, medication and a proper bowel programme, most children keep healthy kidneys and achieve socially acceptable dryness. This is a condition that is managed rather than cured, and the children who do best are the ones whose families keep the routine going and attend the reassessments.
This describes what usually happens, not what will happen to your child. The surgeon will give you a specific picture after examining them.
Can It Be Prevented?
The underlying nerve problem cannot be prevented, though folic acid before and during early pregnancy reduces the risk of spina bifida. Kidney damage from a neurogenic bladder very often can be prevented, and that is the whole point of the treatment.
From First Visit to Going Home
What happens, in order, so that nothing on the day comes as a surprise.
Consultation
Dr. Pratheep Samraj examines your child and goes through the history, earlier reports and any treatment already given.
Investigation
Only the tests that change the decision are asked for — commonly an ultrasound, blood tests, and occasionally an X-ray or a scopy.
Explanation
You are told what the condition is, whether it needs surgery, what happens if you wait, and what the operation involves.
Treatment
If surgery is appropriate it is planned with paediatric anaesthetic cover, with ICU and NICU support available in the hospital.
Follow-up
You go home with written instructions and a review date, and you can reach the hospital by phone or WhatsApp in between.
Hospital stay
Assessment and CIC training are outpatient or short-stay. Reconstructive bladder surgery is a major procedure with a longer admission.
Recovery at home
CIC becomes routine for most families within a few weeks of training. After reconstructive surgery, recovery takes several weeks and lifelong catheterisation is usually part of the plan.
Follow-up
Lifelong, with regular ultrasound, kidney function and urodynamic reassessment as the child grows.
Please bring with you: all previous scan reports, blood test reports, discharge summaries, records of any earlier operation, current medicines, and your child’s immunisation card. Photographs on your phone of a swelling that comes and goes are genuinely useful.
Please note: this page is general information about Neurogenic Bladder, not advice about your child. Timing, suitability for surgery and the expected result differ from child to child and are decided only after clinical evaluation.
Questions Parents Ask
If your question is not here, send it on WhatsApp — you will get an answer from the hospital team.
Dr. Pratheep Samraj
Consultant Paediatric & Neonatal Surgeon · Palliyadi, Kanyakumari
Super-specialist surgical care for newborns, infants and children, with expertise in paediatric urology, congenital anomalies, gastro-intestinal surgery and minimally invasive surgery.
Related Conditions
The bladder can be managed. The kidneys are what we are protecting.
Catheterisation and the right medication keep pressures low, keep the kidneys safe and get most children dry. Bring any previous urodynamic study so the change over time can be seen.
Consultation 10:00 AM - 1:00 PM & 4:00 PM - 8:00 PM · 24-hour laboratory & pharmacy
In an emergency — green vomiting in a baby, a groin swelling that will not go back, severe tummy pain, or a newborn not passing urine or meconium — come straight to the hospital or to your nearest emergency department. Do not wait for a reply to a message.